Showing posts with label Pulmonology. Show all posts

Wednesday, March 7, 2012

Pathogenesis of idiopathic pulmonary fibrosis - 2011 Lancet review

Idiopathic pulmonary fibrosis (IPF) is a devastating, age-related lung disease of unknown cause that has few treatment options.

IPF was once thought to be a chronic inflammatory process, but current evidence indicates that the fibrotic response is driven by abnormally activated alveolar epithelial cells (AECs).


Interstitial Lung Diseases (ILD) (click to enlarge the image).

Alveolar epithelial cells (AECs) produce mediators that induce the formation of fibroblast and myofibroblast foci through:

- proliferation of mesenchymal cells
- attraction of circulating fibrocytes
- stimulation of the epithelial to mesenchymal transition

The fibroblast and myofibroblast foci secrete excessive amounts of extracellular matrix (collagen), resulting in scarring and destruction of the lung architecture.


Mechanisms of IPF (click to enlarge the image). Image source: PLoS Medicine, Creative Commons license.

References:

Idiopathic pulmonary fibrosis. The Lancet, Volume 378, Issue 9807, Pages 1949 - 1961, 3 December 2011.

Interstitial Lung Diseases (ILD)

Thursday, January 26, 2012

How to evaluate a patient with chronic cough?

Initial evaluation of chronic cough (defined as more than 8 weeks' duration in adults and 4 weeks in children) should include a chest radiography (CXR) in most adult patients.

Patients who are taking an angiotensin-converting enzyme inhibitor (ACEi) should switch to a medication from another drug class.


Differential diagnosis of cough, a simple mnemonic is GREAT BAD CAT TOM. Click here to enlarge the image: (GERD (reflux), Laryngopharyngeal Reflux (LPR), Rhinitis (both allergic and non-allergic) with post-nasal drip (upper airway cough syndrome), Embolism, e.g. PE in adults, Asthma, TB (tuberculosis), Bronchitis, pneumonia, pertussis, Aspiration, e.g foreign body in children, Drugs, e.g. ACE inhibitor, CF in children, Cardiogenic, e.g. mitral stenosis in adults, Achalasia in adults, Thyroid enlargement, e.g. goiter, "Thoughts" (psychogenic), Other causes, Malignancy, e.g. lung cancer in adults).

The most common causes of chronic cough in adults are:

- upper airway cough syndrome (post-nasal drip)
- asthma
- gastroesophageal reflux disease (GERD)
- any combination of the above

If upper airway cough syndrome is suspected, a trial of a decongestant and an antihistamine is warranted.

The diagnosis of asthma can be confirmed with a clinical response to empiric therapy with inhaled bronchodilators or corticosteroids (spirometry is generally preferred though).

Empiric treatment for gastroesophageal reflux disease (GERD) should be initiated in lieu of testing for patients with chronic cough and reflux symptoms.

Patients should avoid exposure to cough-evoking irritants, such as cigarette smoke.

Further testing may be indicated if the cause of chronic cough is not identified and includes:

- high-resolution computed tomography (CT) of the chest
- referral to a pulmonologist or an allergist

In children, a cough lasting longer than 4 weeks is considered chronic.

The most common causes of chronic cough in children are:

- respiratory tract infections ("bronchitis" and pneumonia)
- asthma
- rhinitis with post-nasal drip
- gastroesophageal reflux disease (GERD)
- aspirated foreign body is relatively rare but must not be missed

Evaluation of children with chronic cough should include chest radiography (CXR) and spirometry (if older than 5 years of age). Skin prick test for environmental allergies can also be indicated.

References:

Evaluation of the patient with chronic cough. Benich Iii JJ, Carek PJ. Am Fam Physician. 2011 Oct 15;84(8):887-92.

Diagnosis of chronic cough in children

Friday, January 20, 2012

Lung cancer - Lancet review

Small-cell lung cancer

Diagnosis relies on histology, with the use of immunohistochemical studies to confirm difficult cases.

Typical patients are men older than 70 years who are current or past heavy smokers and who have pulmonary and cardiovascular comorbidities.

Patients often present with rapid-onset symptoms due to:

- local intrathoracic tumour growth
- extrapulmonary distant spread
- paraneoplastic syndromes
- a combination of these features

Staging aims ultimately to define disease as metastatic or non-metastatic:

- Combination chemotherapy (platinum-based plus etoposide or irinotecan) is the mainstay first-line treatment for metastatic small-cell lung cancer.

- For non-metastatic disease, early concurrent thoracic radiotherapy is indicated.

Prophylactic cranial irradiation should be considered for all patients, even without metastases, whose disease does not progress after induction chemotherapy and radiotherapy.

Despite high initial response rates, most patients eventually relapse. Except for topotecan, few treatment options then remain.

Non-small-cell lung cancer (NSCLC)

The recently introduced 7th edition of the TNM classification relates better to other prognostic factors such as biological markers.

The advances in treatment include:

- a new generation of chemotherapy agents
- a proven advantage to adjuvant chemotherapy after complete resection for specific stage groups
- new techniques for radiotherapy
- new surgical approaches

References:

Small-cell lung cancer. The Lancet, Volume 378, Issue 9804, Pages 1741 - 1755, 12 November 2011

Non-small-cell lung cancer. The Lancet, Volume 378, Issue 9804, Pages 1727 - 1740, 12 November 2011

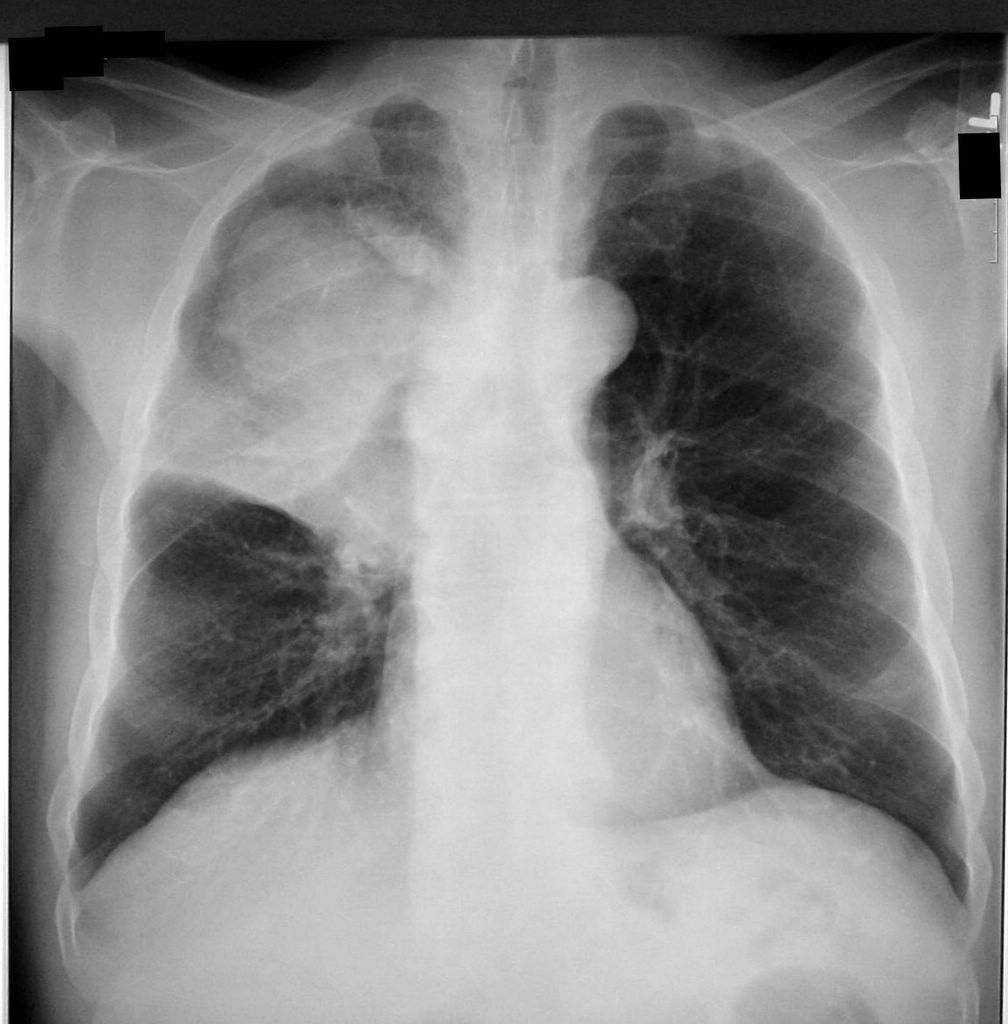
Image source: A CXR shows a right upper lobe (RUL) mass due to lung cancer. Source: Finger Clubbing due to Lung Cancer. Clinical Cases and Images.

Friday, December 23, 2011

George Michael, still breathless after pneumonia and tracheotomy, plans a show for his doctors (video)


Video: George Michael: This has been the worst month of my life. ShowBiz411.

A thin and visibly weak George Michael (48) told reporters outside his home in London that he wasn't supposed to speak for very long and was still recovering from a tracheotomy: "I got streptococca-something... It's a form of pneumonia and they spent three weeks keeping me alive basically," Michael said of the doctors in the Austrian hospital where the singer has been receiving treatment since he fell ill in November.

He added that he also wanted to hold a special show for the Austrian doctors who treated him. "I've spent the last 10 days since I woke up literally thanking people for saving my life."

References:

Gaunt George Michael says "fortunate to be here". Reuters, 2011.

Friday, November 4, 2011

Diagnosis and Management of COPD - Current Guidelines

WHO estimates that 210 million people have COPD worldwide. COPD is the 4th leading cause of death in the world, but by 2030 it is expected to be the 3rd, behind CAD and stroke (http://bit.ly/X5nje). COPD mortality is inversely correlated to the forced expiratory volume (FEV1) in 1 second (http://bit.ly/ZYIR7).

Here are the key recommendations from the recently published Guidelines for management of stable chronic obstructive pulmonary disease (COPD):

1. Spirometry should be obtained to diagnose airflow obstruction in patients with respiratory symptoms. Spirometry should not be used to screen for airflow obstruction in individuals without respiratory symptoms.

2. For stable COPD patients with respiratory symptoms and FEV1 between 60% and 80% predicted, treatment with inhaled bronchodilators may be used.

3. For stable COPD patients with respiratory symptoms and FEV1 <60% predicted, inhaled bronchodilators should be used.

4. Clinicians should prescribe monotherapy using either long-acting inhaled anticholinergics (LAMA) or long-acting inhaled β-agonists (LABA) for symptomatic patients with COPD and FEV1 <60% predicted.

5. Clinicians may administer combination inhaled therapies (long-acting inhaled anticholinergics, long-acting inhaled β-agonists, or inhaled corticosteroids, LABA/ICS) for symptomatic patients with stable COPD and FEV1<60% predicted.

6. Clinicians should prescribe pulmonary rehabilitation for symptomatic patients with an FEV1 <50% predicted. Clinicians may consider pulmonary rehabilitation for symptomatic or exercise-limited patients with an FEV1 >50% predicted.

7. Clinicians should prescribe continuous oxygen therapy in patients with COPD who have severe resting hypoxemia (PaO2 ≤55 mm Hg or SpO2 ≤88%).

References:

Diagnosis and Management of Stable Chronic Obstructive Pulmonary Disease: A Clinical Practice Guideline Update from the American College of Physicians, American College of Chest Physicians, American Thoracic Society, and European Respiratory Society. ACP, 08/2011. Annals of Int Medicine, 2011.

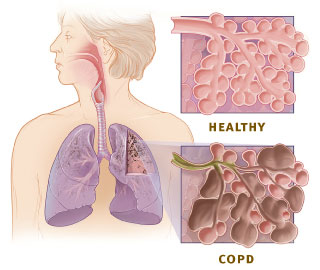
Image source: Enlarged view of lung tissue showing the difference between healthy lung and COPD, Wikipedia, public domain.

Thursday, August 11, 2011

Secondhand smoke is nothing to kid about - CDC video


CDC: This 30-second TV ad features vignettes of children talking about when they're exposed to secondhand smoke. As the narrator points out, secondhand smoke is nothing to kid about. It can hurt lung growth and damage lung function in children. When smoking around your kids, it's like they're smoking.

Wednesday, July 27, 2011

What happens when you ask for medical advice on Twitter - CNN's Anderson Cooper knows from experience

What happens when you ask for medical advice on Twitter and you are CNN's host Anderson Cooper with 1.5 million followers:

Anderson Cooper
Anderson Cooper

Replies:

@thehighsign I generally just go with the opinion of a million and a half strangers.

@SashaTalebi Crazy times we're living in when @andersoncooper can crowdsource his bronchitis diagnosis via Twitter. Get well soon.

@JPLondon72 When a doctor says "You have bronchitis". Usually. Not always.

@emokidsloveme I feel like @andersoncooper has health insurance. Call me crazy, but I think he could afford to pay out of pocket too. #TwitterER

@Technikohler But why don't you just hit up good ole Gupta and ask him ?

@SadaoTurner hey @sanjayguptaCNN, do u know this guy @andersoncooper

@sherrybutlerpr Tight breathing, Burning in chest, fever. B careful, walking pneumonia

@LizaLizzieHalim i knew when i had troubled breathing&it makes sounds.Then i get the doctor checked&was diagnosed with it. Still have it now.

@lynngosselin I've had bronchitis many times so yes I know...but maybe a Dr. will pick up your post

@feathersong Two words - doctor, antibiotics. Make that three words - stat. Feel better soon, you've got a show to do!

@EldinaV And use a mist vaporizer in your dream and lots of OJ

@teresac8 fever, cough, wheezing and irritated breathing but to be sure see a doctor.

@cheeki3 well you want to the homeopathic route. Oregano oil (diluted in juice) will knock it right out.#justsaying

@sherrybutlerpr Also coughing up phlegm. Get on meds. U don't slow down, so will need that or will really go down. Take good care.

Acute bronchitis: Many patients expect to be treated with antibiotics and cough meds but this differs from guidelines


Mind map of differential diagnosis of cough. See more Allergy and Immunology mind maps here.

Cough is the most common symptom bringing patients to the primary care physician's office. The most common diagnosis in these patients is acute bronchitis, according to a recent review in the official journal of AFP, American Family Physician.

Acute bronchitis should be differentiated from other common causes of cough such as pneumonia and asthma - because the therapies are clearly different.

Symptoms of acute bronchitis typically last 3 weeks. As we already know, the presence of colored (e.g., yellow or green) sputum does not reliably differentiate between bacterial and viral lower respiratory tract infections. This statement was contradicted by a recent study: Green or yellow phlegm likely to be bacterial - confirming beliefs by doctors and patients alike (http://goo.gl/zff8X and http://goo.gl/cwKGs).

Viruses cause more than 90% of acute bronchitis, and therefore, antibiotics are generally not indicated. They should be used only if pertussis is suspected to reduce transmission or if the patient is at increased risk of developing pneumonia (e.g., patients 65 years or older).

The typical therapies that have been traditionally used for managing acute bronchitis symptoms have been shown to be ineffective. The U.S. Food and Drug Administration recommends against using cough and cold preparations in children younger than 6 years.

The supplement pelargonium may help reduce symptom severity in adults.

Many patients expect to be treated with antibiotics and cough medications but this differs from evidence-based recommendations.

References:
Diagnosis and treatment of acute bronchitis. Albert RH. Am Fam Physician. 2010 Dec 1;82(11):1345-50.

Tuesday, June 7, 2011

CPAP for sleep apnea - BMJ video


BMJ: Sleep apnoea (apnea, in its American spelling) is a condition that causes a patient to stop breathing for short periods during their sleep. In this video researchers Joaquín Durán-Cantolla and Jose María Montserrat discuss their work into the use of CPAP (continuous positive airway pressure) to treat the condition.

People with OSA may be twice as likely to develop a stroke.

Did you know that obstructive sleep apnea (OSA) can reduce a child’s IQ by as many as 10 points, while treatment in children with OSA can improve school grades?

Related:

Mavs Fan at the Finals - Photos - SI.com http://goo.gl/tIdL3

Understanding PAP Therapy for your Sleep Apnea - video from Cleveland Clinic (2013):

Wednesday, February 23, 2011

Acute bronchitis: Many patients expect to be treated with antibiotics and cough meds but this differs from guidelines


Mind map of differential diagnosis of cough. See more Allergy and Immunology mind maps here.

Cough is the most common symptom bringing patients to the primary care physician's office. The most common diagnosis in these patients is acute bronchitis, according to a recent review in the official journal of AFP, American Family Physician.

Acute bronchitis should be differentiated from other common causes of cough such as pneumonia and asthma - because the therapies are clearly different.

Symptoms of acute bronchitis typically last 3 weeks. As we already know, the presence of colored (e.g., yellow or green) sputum does not reliably differentiate between bacterial and viral lower respiratory tract infections. This conclusion was contradicted by a recent study: Green or yellow phlegm likely to be bacterial - confirming beliefs by doctors and patients alike (http://goo.gl/zff8X and http://goo.gl/cwKGs).

Viruses cause more than 90% of acute bronchitis, and therefore, antibiotics are generally not indicated. They should be used only if pertussis is suspected to reduce transmission or if the patient is at increased risk of developing pneumonia (e.g., patients 65 years or older).

The typical therapies that have been traditionally used for managing acute bronchitis symptoms have been shown to be ineffective. The U.S. Food and Drug Administration recommends against using cough and cold preparations in children younger than 6 years.

The supplement pelargonium may help reduce symptom severity in adults.

Many patients expect to be treated with antibiotics and cough medications but this differs from evidence-based recommendations.

The CNN video below tries to decipher what hides behind the names of common cough and cold medications:


References:
Diagnosis and treatment of acute bronchitis. Albert RH. Am Fam Physician. 2010 Dec 1;82(11):1345-50.

Friday, January 21, 2011

STOP-BANG questionnaire identifies patients with OSA at hight risk for surgical complications

What is preoperative STOP-BANG?

This is a questionnaire that evaluates the following patient characteristics:

Snoring, Tiredness during daytime, Observed apnea, high blood Pressure, Body mass index, Age, Neck circumference, Gender

Patient population

135 adult patients undergoing elective surgery at a tertiary care center were administered the STOP-BANG questionnaire.

41.5% of patients had high risk scores for OSAS.

Patients at high risk of OSAS had a much higher rate of postoperative complications compared with patients at low risk (19.6% vs 1.3%).

STOP-BANG questionnaire predicts high risk

The STOP-BANG questionnaire is useful for preoperative identification of patients at higher than normal risk for surgical complications, probably because it identifies patients with occult OSAS.

References

Obstructive Sleep Apnea Syndrome and Postoperative Complications. Clinical Use of the STOP-BANG Questionnaire. Tajender S. Vasu, MD; Karl Doghramji, MD; Rodrigo Cavallazzi, MD; Ritu Grewal, MD; Amyn Hirani, MD; Benjamin Leiby, PhD; Dimitri Markov, MD; David Reiter, MD; Walter K. Kraft, MD; Thomas Witkowski, MD. Arch Otolaryngol Head Neck Surg. 2010;136(10):1020-1024. doi:10.1001/archoto.2010.1020

Image source: Wikipedia, public domain.

Wednesday, January 19, 2011

Participation in clean-up of oil spill associated with airway injury and chromosomal damage

In 2002, the oil tanker Prestige spilled more than 67 000 tons of bunker oil, heavily contaminating the coast of northwestern Spain. The study population included local fishermen who were highly exposed (n = 501) or not exposed (n = 177) to oil. They were evaluated 2 years after the spill.

Elevated markers of airway injury

Persons exposed to oil were at increased risk for lower respiratory tract symptoms (risk difference, 8.0). However, lung function did not significantly differ between the groups. Exposed participants also had higher levels of exhaled vascular endothelial growth factor (risk difference, 44.8) and basic fibroblast growth factor (risk difference, 16.0).

Human chromosomes (grey) capped by telomeres (white). Image source: Wikipedia, public domain.

Chromosomal damage

A higher proportion of exposed participants had structural chromosomal alterations (risk difference, 27.4), predominantly unbalanced alterations.

Participation in clean-up of a major oil spill was associated with persistent respiratory symptoms, elevated markers of airway injury in breath condensate, and chromosomal damage.

References:
Health Changes in Fishermen 2 Years After Clean-up of the Prestige Oil Spill. Ann Intern Med, October 19, 2010, vol. 153 no. 8 489-498.

After a lung transplant, an aria: a story of survival from end-stage pulmonary hypertension


TED talks: "You'll never sing again, said her doctor. But in a story from the very edge of medical possibility, operatic soprano Charity Tillemann-Dick tells a double story of survival -- of her body, from a double lung transplant -- and of her spirit, fueled by an unwavering will to sing. A powerful story from TEDMED 2011."

Tillemann-Dick was diagnosed in 2004 – at the age of 20 – with Idiopathic Pulmonary Hypertension, a disease that causes high blood pressure in the pulmonary artery, which connects the heart to the lungs. People with the disease typically have a two-to-five-year mortality rate after diagnosis.

Her physicians at Johns Hopkins put her on the lung transplant list at Cleveland Clinic. In September 2009, organs became available, and she had a double lung transplant. After a 13-hour surgery and 2 cardiac arrests in the OR, her recovery was extremely complicated but she is happy to be able to sing again.

If you have a minute, don't forget to check the comments on YouTube and the TED Talks site.

References:
Faith, Hope... and Charity. Cleveland Clinic.

Monday, December 13, 2010

COPD patients with anxiety have a higher risk of exacerbations

Psychological functioning is an important determinant of health outcomes in chronic lung disease.

COPD was associated with a greater risk of anxiety in multivariable analysis (OR 1.85). Among patients with COPD, anxiety was related to poorer health outcomes including worse submaximal exercise performance (less distance walked during the 6-min walk test) and a greater risk of self-reported functional limitations.

Subjects with COPD with anxiety had a higher risk of COPD exacerbations.

COPD is associated with a higher risk of anxiety. Once anxiety develops among patients with COPD, it is related to poorer health outcomes.

References:

Influence of anxiety on health outcomes in COPD. Eisner et al. Thorax 2010;65:229-234 doi:10.1136/thx.2009.126201
Action plan is a key component of self-management programs in patients with COPD. Thorax, 20111.

Comments:

Dr RW: I don't have the full text of this paper, and I wonder if they controlled for continued smoking. Nicotine is a powerful anxiolytic for some COPD patients.

Thursday, October 21, 2010

New CPR Guidelines - Hands Only - Use "CAB" Instead of "ABC" While Singing "Stayin' Alive"


The American Heart Association is adopting new cardiopulmonary Resuscitation (CPR) guidelines that do away with mouth to mouth resuscitation and focus on chest compressions. Do fast, forceful compressions; the beat of "Stayin' Alive" is the right pace - 100 beats per minute. Queen's "Another one bites the dust" was rejected as an alternative song choice.

Currently, this recommendation only applies to laymen CPR. The professional rescuers (EMTs, doctors, etc.) should use the previous approach with a compression-breathing (ventilation) ratio of 30:2.

However, “chest compression only” CPR is recommended if the rescuer is not trained (for example, in dispatcher assisted CPR) or is not willing to give rescue breaths. The aim is now to compress the chest to a depth of 5-6 cm (rather than 4-5 cm). This recommendation is based on several studies showing that deeper compressions were associated with improved short term outcomes.


Dr. Sanjay Gupta shows Matthew McConaughey the new way of doing CPR on Larry King Live.


Bee Gees - Stayin' Alive.

References:

New CPR is spelled C-A-B. CNN.
New international guidelines on resuscitation. BMJ, 2010.

Related reading:

Dangers of unrecognized heart disease: Husband dies while giving wife CPR (both found dead, age 60, 59) http://goo.gl/LZ39U
British Heart Foundation is urging people to forget "mouth-to-mouth" during CPR: 'no kissing, just hard CPR'. BBC, 2011.

Thursday, October 7, 2010

What's new in pulmonary, critical care, and sleep medicine from UpToDate

35% of UpToDate topics are updated every four months. The editors select a small number of the most important updates and share them via "What's new" page. I selected the brief excerpts below from What's new in hematology:

Asthma

When evaluating patients for occupational asthma, sputum eosinophil counts at 7 and 24 hours after specific inhalation challenge have a greater sensitivity and positive predictive value than exhaled nitric oxide (eNO).

Critical care

Proton pump inhibitors (PPIs) may be slightly more effective than histamine-2 (H2) blockers at preventing gastrointestinal (GI) bleeding in critically ill patients. However, the difference is small if real.

Idiopathic pulmonary fibrosis

Sildenafil, tyrosine kinase inhibitor imatinib, and pirfenidone, an anti-fibrotic agent, were each no more effective than placebo for treatment of idiopathic pulmonary fibrosis.

Pleural effusion

Using ultrasonography to identify a site for diagnostic thoracentesis is associated with significantly lower risk of pneumothorax, than using the physical exam for site selection.

Pulmonary embolism

PE is frequently asymptomatic. Among 5233 patients with a DVT, 32 percent had asymptomatic PE.

References:
What's new in pulmonary, critical care, and sleep medicine. UpToDate.

Wednesday, October 6, 2010

First official antismoking campaign was launched in 1604 by James I of England

From the BMJ:

Monarchs and their heirs are not always noted for their rational medical advice. But James VI of Scotland, who became James I of England in 1603, was different.

Published anonymously in 1604 but immediately credited to the king, A Counterblaste to Tobacco flew in the face of prevailing medical opinion by outlining some of the chief health risks of smoking more than three centuries before scientists made the connection.

Possibly the first official antismoking campaign, the royal pamphlet highlighted cost and passive smoking as two of the most powerful arguments against tobacco, while it lamented that addiction, peer pressure, and fashion were among the most difficult obstacles to overcome.


A Counterblaste to Tobacco is written in Early Modern English and refers to medical theories of the time (e.g. the four humours). In it, King James I blames Native Americans for bringing tobacco in Europe, complains about passive smoking, warns of dangers to the lungs, and decries tobacco's odour as "hatefull to the nose."

James's dislike of tobacco led him to authorize an excise tax and tariff of six shillings and eight pence per pound of tobacco imported, or £1 per three pounds, a large sum of money for the time.

References:
Royal insights on smoking - Moore 340: c1408 - BMJ.
Image source: James I, VI by John de Critz, c.1606, Wikipedia, public domain.
A Counterblaste to Tobacco. Wikipedia.

Twitter comments:

@CardioNP: 400+ yrs later I still wade thru smoke to enter the hospital.

Tuesday, August 17, 2010

2 in 3 people with known risk factors for COPD don't know they have the disease

One in five heavy smokers over age 40 have findings of COPD, but only one-third have been previously diagnosed with the common lung disease.

10% of people worldwide over the age of 40 are affected by COPD.

Researchers screened 1,003 people aged 40 and over who were current or former heavy smokers. Heavy smoking was defined as a smoking history of 20 pack-years or more.

The results showed that 20.7% of the people screened met the criteria for a diagnosis of COPD but only 32.7% had previously been diagnosed with the disease or were aware of their COPD diagnosis.

References:
Many Unaware They Have COPD. WebMD.
Image source: Lungs, Wikipedia, public domain.

Tuesday, July 27, 2010

Video: Awake Endotracheal Intubation


Video: Awake Endotracheal Intubation for "Fun and Knowledge" by an anesthesiologist from the Massachusetts General Hospital (MGH). Not sure about the "fun" part...

References:
Awake Endotracheal Intubation for Fun and Knowledge. Medgadget, 2010.

Tuesday, May 11, 2010

17% of food-related asphyxiations were caused by hot dogs - "the perfect plug for a child's airway"

From Consumer Reports health blog:

Small toys and foods that are choking hazards should carry warning labels - and some hot dog brands already do.

About 17% of food-related asphyxiations were caused by hot dogs. In total, 41% were caused by food items including:

- hot dogs
- grapes
- carrots
- hard candy

Food manufacturers should design new foods and redesign existing foods to avoid shapes, sizes, textures and other characteristics that increase choking risk to children, to the extent possible.

"If you were to take the best engineers in the world and try to design the perfect plug for a child's airway, it would be a hot dog," says statement author Gary Smith. "I'm a pediatric emergency doctor, and to try to get them out once they're wedged in, it's almost impossible."

References:
Image source: Wikipedia, GNU Free Documentation License.

Related:
Kinder Surprise egg seized at U.S. border - banned by law as a choking hazard to young children http://goo.gl/UNUoG - Sold around the world.

Sunday, May 2, 2010

Tiotropium for COPD: A good foundation therapy for most patients

From a BMJ Editorial:

Tiotropium is a once daily, inhaled, long acting anticholinergic drug (LAMA) that provides 24 hour improvement in airflow and hyperinflation in patients with chronic obstructive pulmonary disease (COPD).

Clinical trials have consistently shown that these physiological effects translate into improvements in:

- lung function
- exercise tolerance
- health related quality of life
- fewer exacerbations

References:
Tiotropium and chronic obstructive pulmonary disease. BMJ, 2010.
http://www.bmj.com/cgi/content/short/340/feb19_1/c833
Image source: Wikipedia, public domain.